
ME/CFS diagnosis: how is ME/CFS established?
ME/CFS is diagnosed clinically, using established criteria and by ruling out other causes. Which lab values are checked, what the blood test debate is about, and where to turn.
Short answer
ME/CFS is a clinical diagnosis: it rests on established criteria and on ruling out other conditions.
Lab values do not prove ME/CFS, but they help rule out treatable causes with similar symptoms.
There is no single approved blood test for ME/CFS yet – though there is promising research.
Post-exertional malaise (PEM) is a central criterion for the diagnosis.
One of the most common questions about ME/CFS is: is there a test for it? The short answer: ME/CFS is diagnosed clinically – through established criteria and by ruling out other causes. So far there is no single approved lab test that proves the illness. This page explains the diagnostic path, which lab values play a role, what is behind the much-discussed blood test, and where to turn.
Key points
Diagnosis via clinical criteria (e.g. Canadian Consensus Criteria, IOM 2015).
Lab work serves exclusion, not proof.
PEM is a central, usually required criterion.
Diagnosis often takes years – good documentation helps.
Editorial responsibility
Elara Health
Patient-centered health information
Last updated
September 13, 2026
ME/CFS self-test and everyday support
Use questionnaires when explanation should turn into structured symptom capture, diagnostic orientation, or severity documentation.
ME/CFS symptom check
Best when the main question is whether the symptom pattern fits ME/CFS-oriented criteria.
FUNCAP-27 questionnaire
Use when function, daily limitation, and severity need clearer structure over time.
Compare pacing apps
Compare symptom diaries, wearable support, and costs to find a tool for your daily routine.
ME/CFS is a clinical diagnosis of exclusion
Unlike many conditions, there is no single value that proves ME/CFS. Instead it is diagnosed clinically: based on the typical symptom pattern, established diagnostic criteria, and the exclusion of other conditions that can cause similar complaints.
The central criterion is post-exertional malaise (PEM) – the delayed, disproportionate worsening after physical, cognitive, or emotional exertion. Without PEM, the diagnosis is generally not made under the common criteria.
Which lab values are checked in ME/CFS?
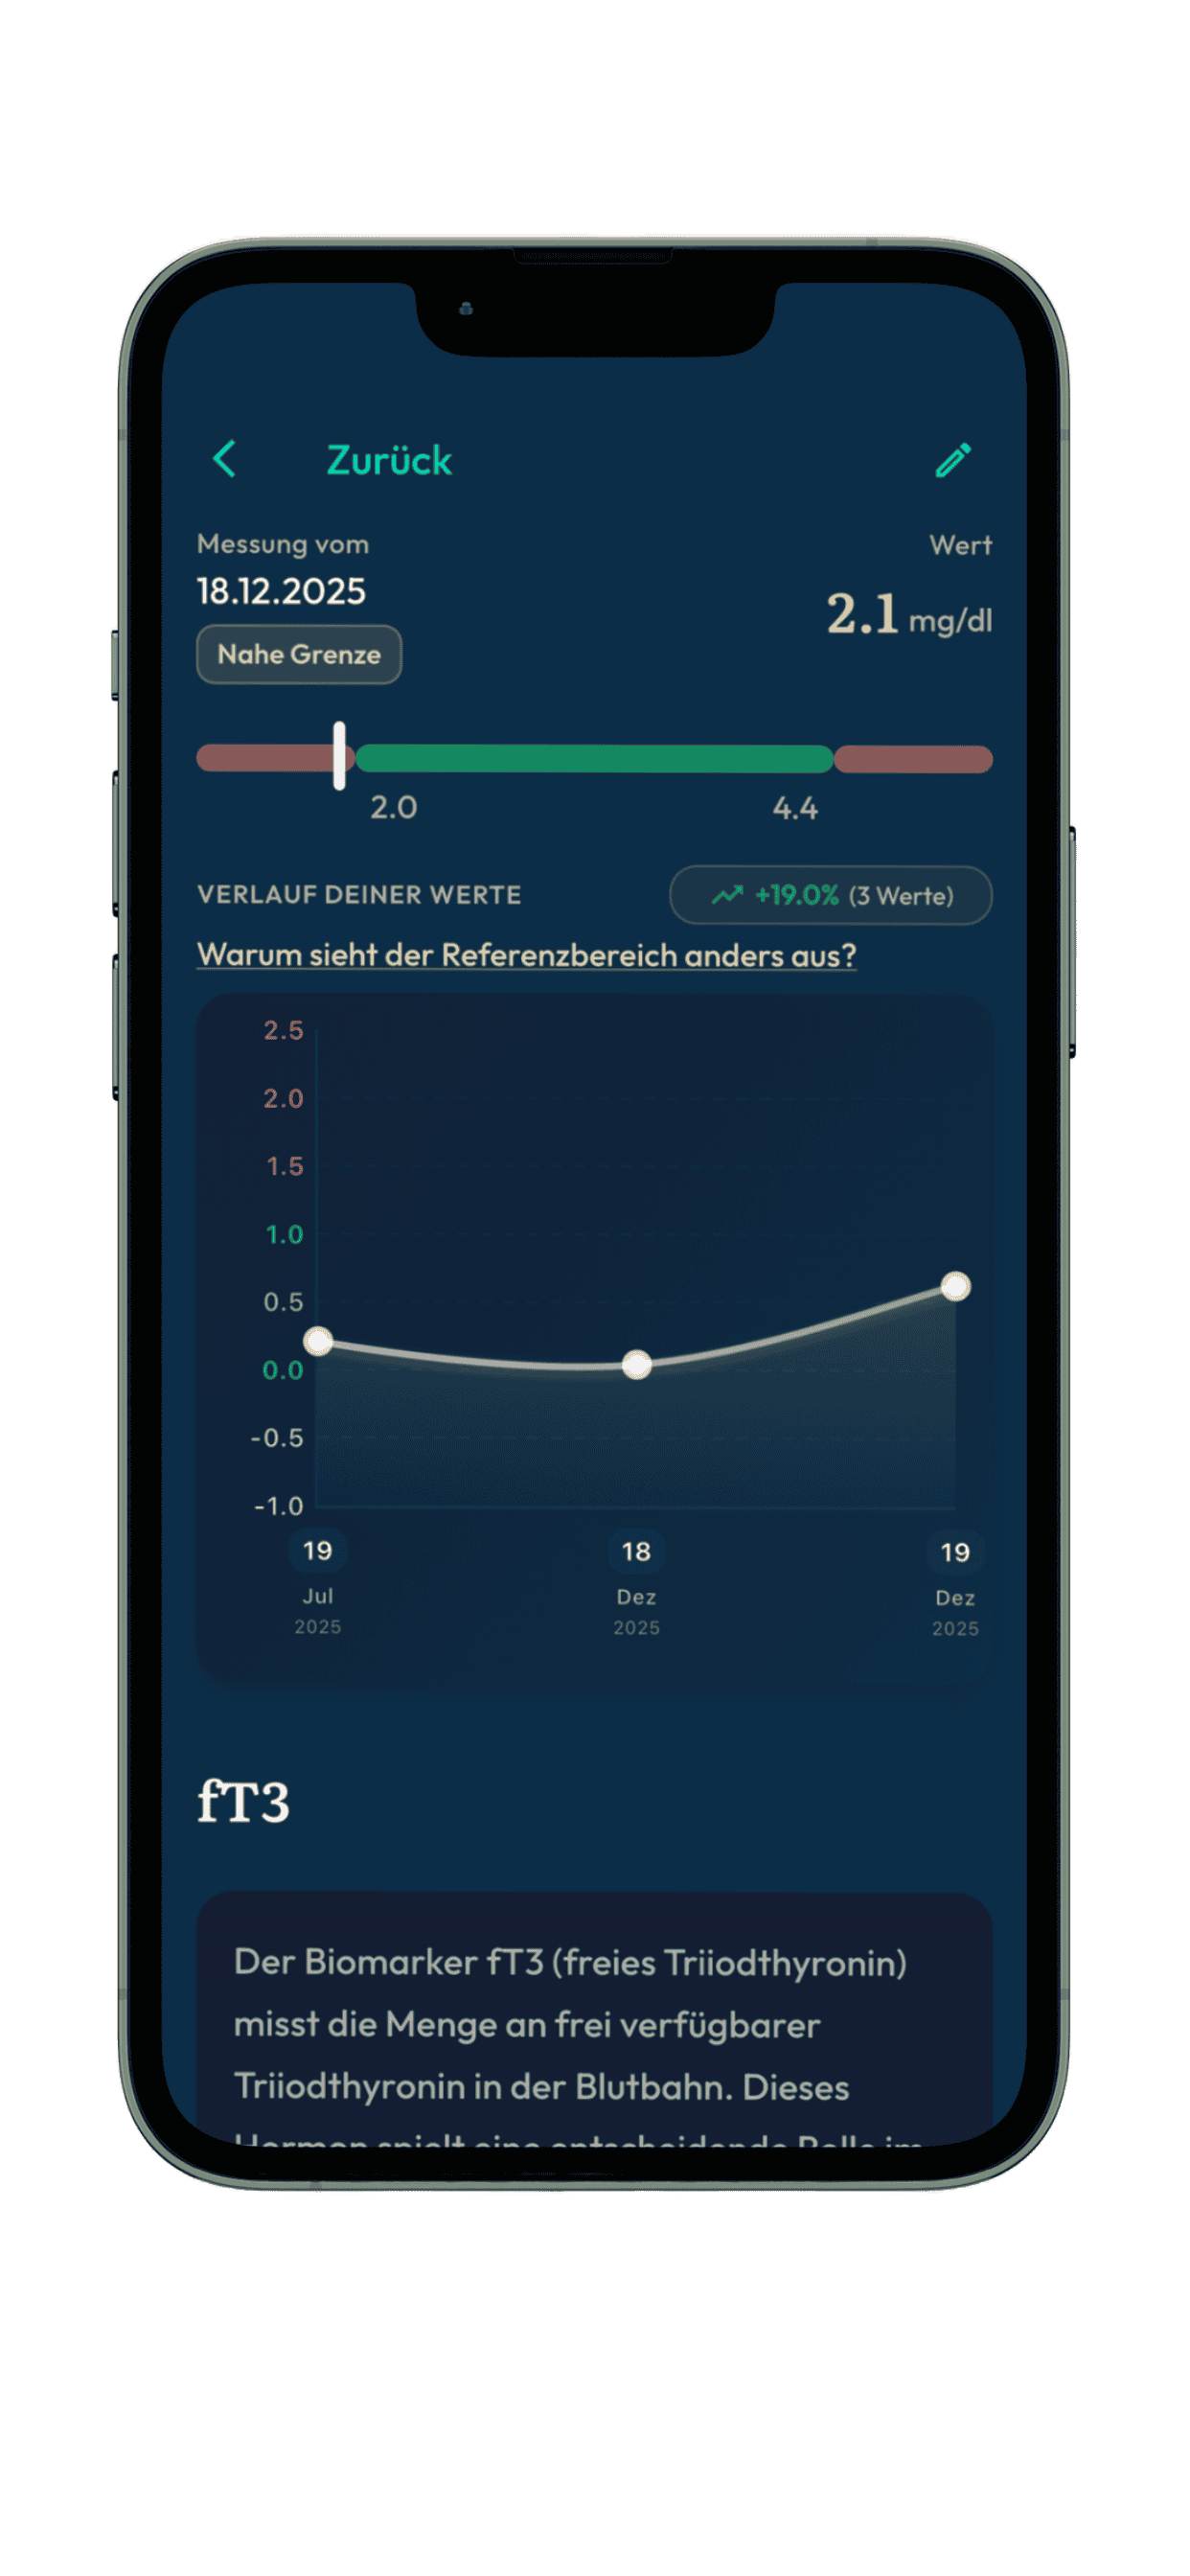
Lab values cannot detect ME/CFS, but they are important for identifying or ruling out treatable causes with similar symptoms – such as iron deficiency, thyroid disorders, vitamin deficits, inflammation, or metabolic and autoimmune conditions. Which values are measured, with reference ranges, can be found on the respective biomarker pages.
A typical exclusion panel is broader than for simple fatigue. Commonly checked are, among others:
Blood count and inflammation values (CRP, ESR)
Ferritin and iron status
Thyroid (TSH, fT3/fT4 if needed)
Vitamin D, vitamin B12, and folate
Liver and kidney values, electrolytes, blood sugar
EBV and, if needed, further viral serology
If needed: cortisol, immunoglobulins, coeliac or autoimmune markers
Is there a blood test for ME/CFS? (As of 2026)
The search for an objective biomarker is one of the most active research areas. In 2025 and 2026 several promising approaches were published – including an epigenetic blood test that reached high accuracy in a study, as well as various protein and metabolic markers.
Important context: these tests are at the research stage. As of 2026 there is no broadly approved, clinically established blood test that replaces an ME/CFS diagnosis. Anyone who encounters such offers should interpret them critically and in discussion with a doctor.
The diagnostic criteria in brief
Internationally used are the Canadian Consensus Criteria (CCC, 2003) and the criteria of the US Institute of Medicine (IOM/NAM, 2015), which established PEM as a required core criterion. Both combine reduced capacity, PEM, unrefreshing sleep, and cognitive or autonomic symptoms.
How these patterns can be captured in a structured way is described in more detail on our page about symptoms and diagnostic criteria.
Why diagnosis often takes years
Many people report a long medical odyssey before ME/CFS is recognized. Complaints are often first attributed to burnout, depression, or “just stress,” and specialized centers are limited.
Structured documentation of symptoms, exertion, and especially PEM responses can ease the diagnostic path. It makes visible patterns that would otherwise get lost in a short appointment, and prepares the conversation more precisely.
Which doctors and centers can help
The first point of contact is usually the GP, who can initiate the exclusion work-up. For further assessment there are specialized centers such as the Charité Fatigue Centrum – though their capacity is limited and partly regionally restricted.
The German Society for ME/CFS provides information for physicians and a practice guide developed together with Charité. These materials can help support your own care team on the topic of ME/CFS.
More context
More detail when you need it.
Medication and lab values can sit beside the rest of your history without crowding the pacing flow.
Structure daily life with ME/CFS
Record symptoms, exertion, and recovery to understand your trajectory – with the Elara app.
FAQ
Is there a blood test for ME/CFS?
As of 2026 there is no broadly approved, clinically established blood test that proves ME/CFS. There is promising research, for example on epigenetic and protein biomarkers, but it is still at the research stage.
Which blood values are tested in ME/CFS?
Mainly values to rule out other causes: blood count, inflammation values, ferritin, thyroid (TSH), vitamin D, vitamin B12, liver and kidney values, and EBV serology. They do not prove ME/CFS but help identify treatable conditions.
Which doctor makes the ME/CFS diagnosis?
A GP can start the work-up. Specialized centers such as the Charité Fatigue Centrum are helpful but have limited capacity. What matters is a medical assessment based on the criteria.
Is ME/CFS a diagnosis of exclusion?
Yes. ME/CFS is made clinically via established criteria, after other conditions with similar symptoms have been ruled out.
Does PEM have to be present for the diagnosis?
Under the common criteria, PEM is a central, usually required feature. The delayed worsening after exertion is therefore a key part of the diagnosis.
How long does it take to get a diagnosis?
Often several years. Symptoms are frequently attributed to something else at first, and specialized centers are limited. Good symptom and PEM documentation can shorten the path.
Can a GP diagnose ME/CFS?
Yes, in principle this is possible. What matters is applying the criteria, ruling out other causes, and experience with the condition. Professional materials and specialized centers can provide support.
Editorial standards
The linked guidelines and institutional resources explain the medical background. Editorial responsibility and any documented medical review are identified separately.
Medical background: 4 sources
Educational context – not a substitute for medical diagnosis
Links to related knowledge, questionnaires, and methodology
Guidelines and medical background
CDC — Clinical overview of ME/CFS
Open source
NICE NG206 — ME/CFS: diagnosis and management
Open source
Charité Fatigue Centrum (CFC)
Open source
German Society for ME/CFS
Open source