
Can Long COVID turn into ME/CFS?
When a Long COVID course starts to look more like ME/CFS – and why PEM, reduced capacity, and recovery patterns matter so much.
Short answer
Yes, Long COVID can evolve into a course that strongly resembles ME/CFS.
This becomes especially relevant when PEM, clearly reduced capacity, brain fog, and impaired recovery after activity shape the picture.
What matters most is not the label alone, but the pattern of exertion response, symptom course, and daily function.
Many people notice that post-COVID symptoms do not only persist, but begin to form a pattern that looks increasingly like ME/CFS. For affected people, that transition question is often more useful than a purely semantic debate.
What matters most
Long COVID is a broad umbrella term, while ME/CFS is a more specific illness pattern.
PEM is one of the strongest clues that the course is becoming more ME/CFS-like.
Not every persistent post-COVID symptom pattern automatically equals ME/CFS.
In practical terms, the question matters most when activity repeatedly leads to clear setbacks.
Editorial responsibility
Elara Health
Patient-centered health information
Last updated
September 13, 2026
ME/CFS self-test and everyday support
Use questionnaires when explanation should turn into structured symptom capture, diagnostic orientation, or severity documentation.
ME/CFS symptom check
Best when the main question is whether the symptom pattern fits ME/CFS-oriented criteria.
FUNCAP-27 questionnaire
Use when function, daily limitation, and severity need clearer structure over time.
Compare pacing apps
Compare symptom diaries, wearable support, and costs to find a tool for your daily routine.
Why this question comes up so often
Many people begin with persistent symptoms after infection and only later notice that capacity keeps shrinking, recovery gets harder, and activity triggers worsening hours or days later.
That is often the point where the course starts to feel less like a broad Long COVID label and more like a specific ME/CFS pattern.
Which patterns suggest a more ME/CFS-like course
The most important clue is PEM: disproportionate and often delayed worsening after physical, cognitive, or emotional exertion.
Other common features include markedly reduced capacity, brain fog, sleep problems, orthostatic symptoms, or the feeling that even small demands have outsized consequences.
PEM or clearly exertion-linked crashes
markedly reduced capacity
cognitive worsening after activity
recovery stretched across several days
Why this matters in daily life
If the course becomes more ME/CFS-like, the most useful daily strategies often change. Careful load management, pacing, and better longitudinal tracking become much more important.
The point is not to collapse every post-COVID case into one label, but to take PEM and exertion response seriously enough to change decisions.
More context
More detail when you need it.
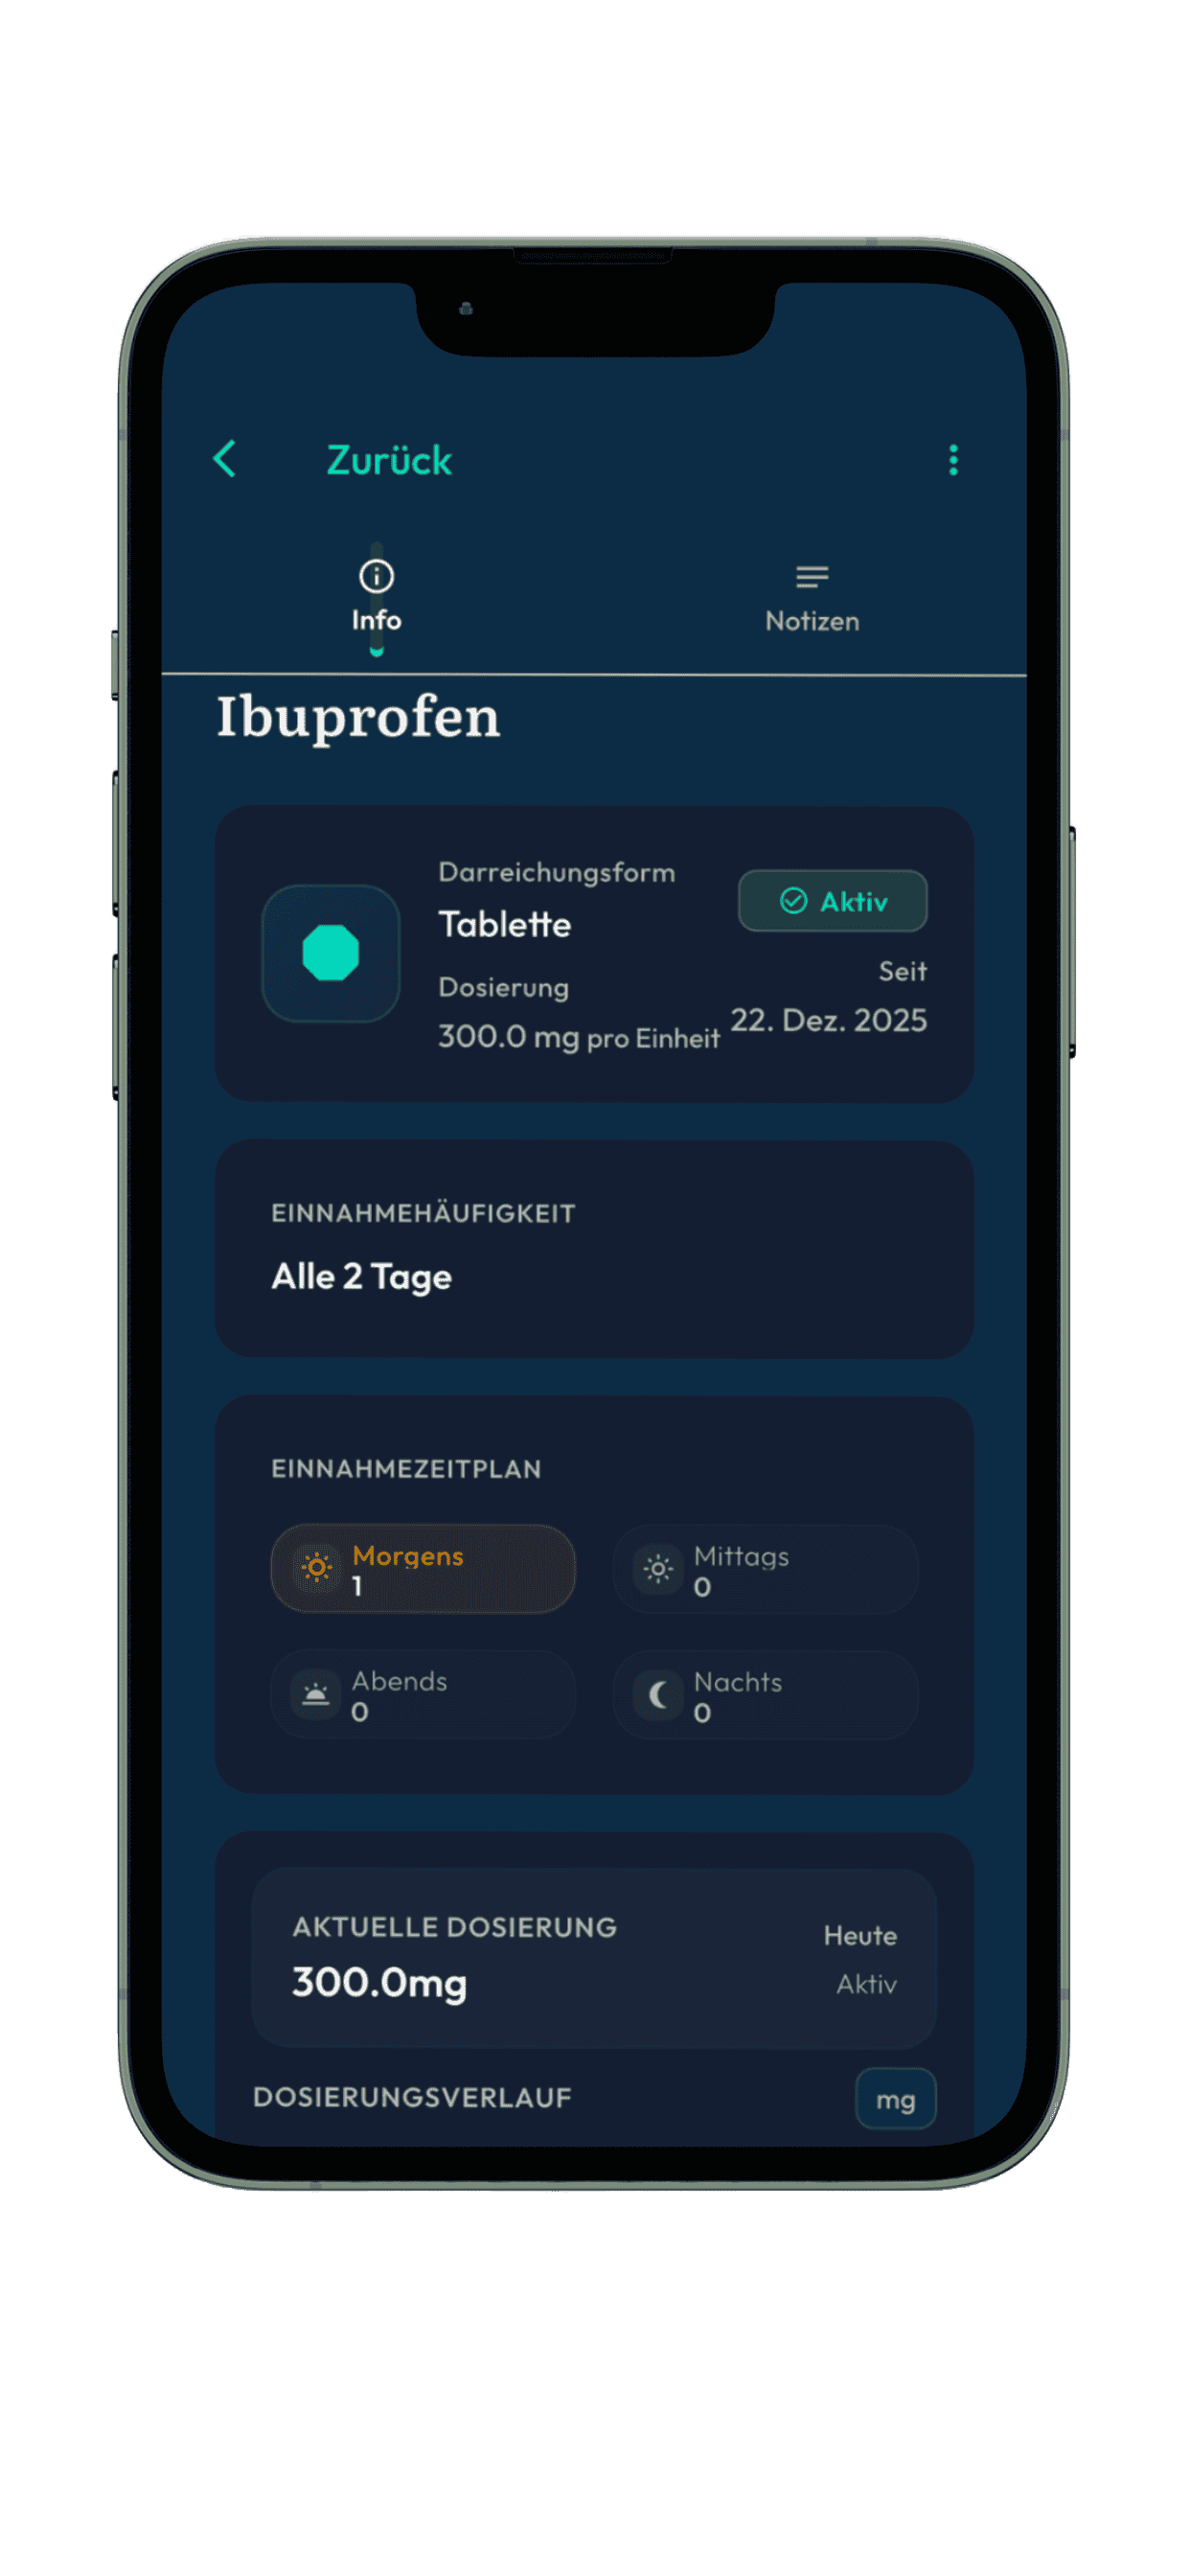
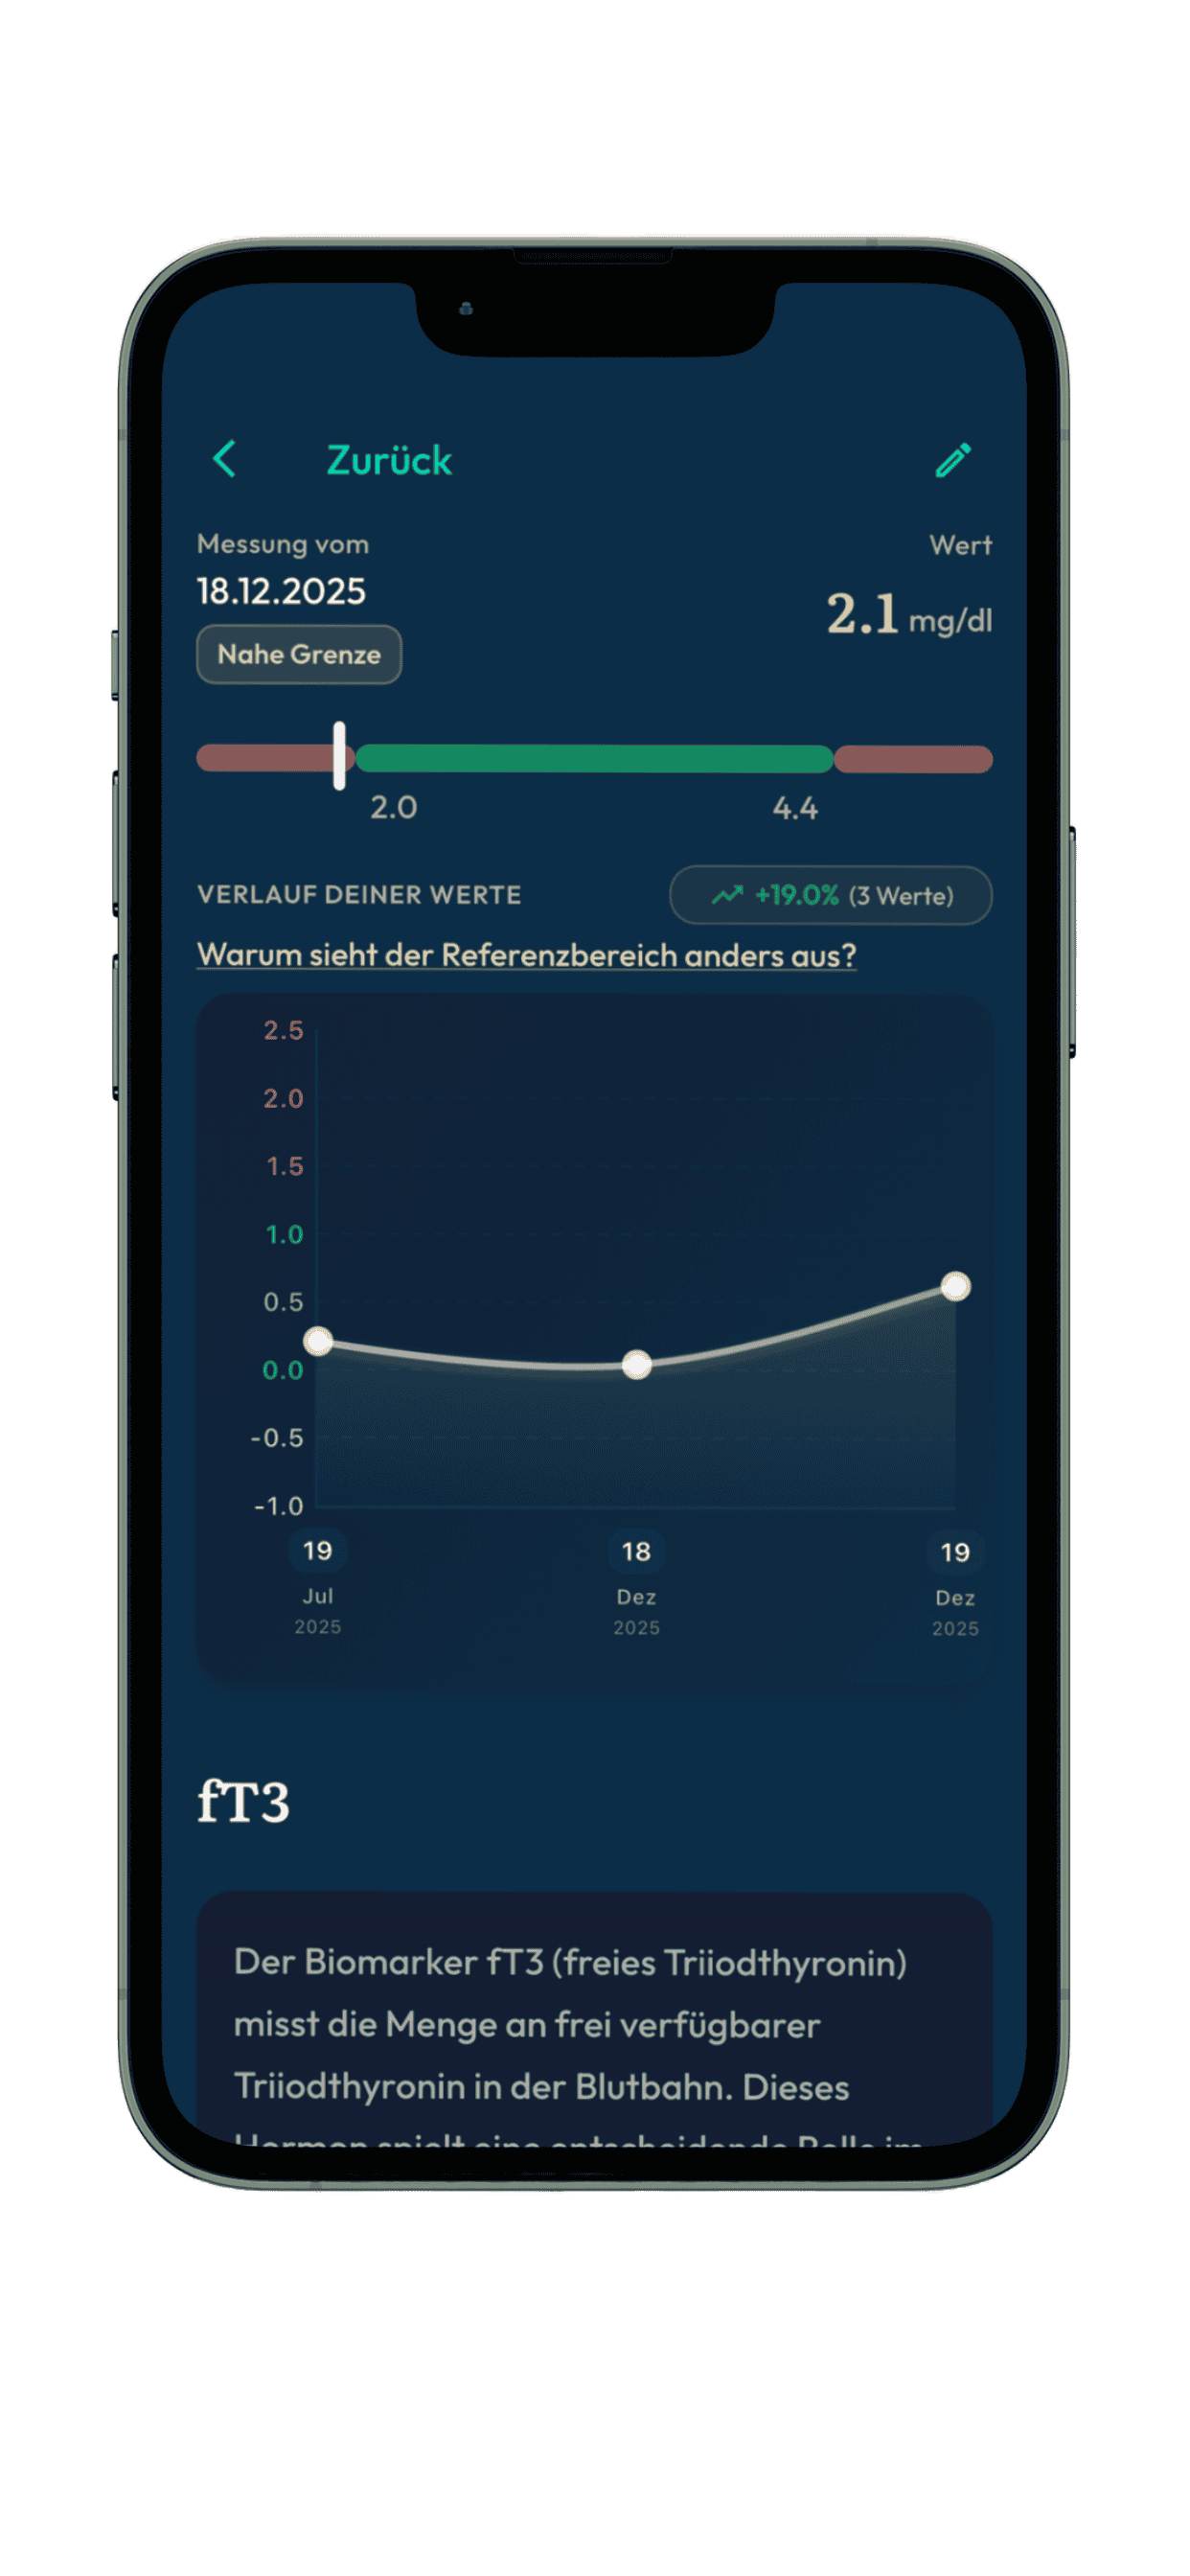
Medication and lab values can sit beside the rest of your history without crowding the pacing flow.
Structure daily life with ME/CFS
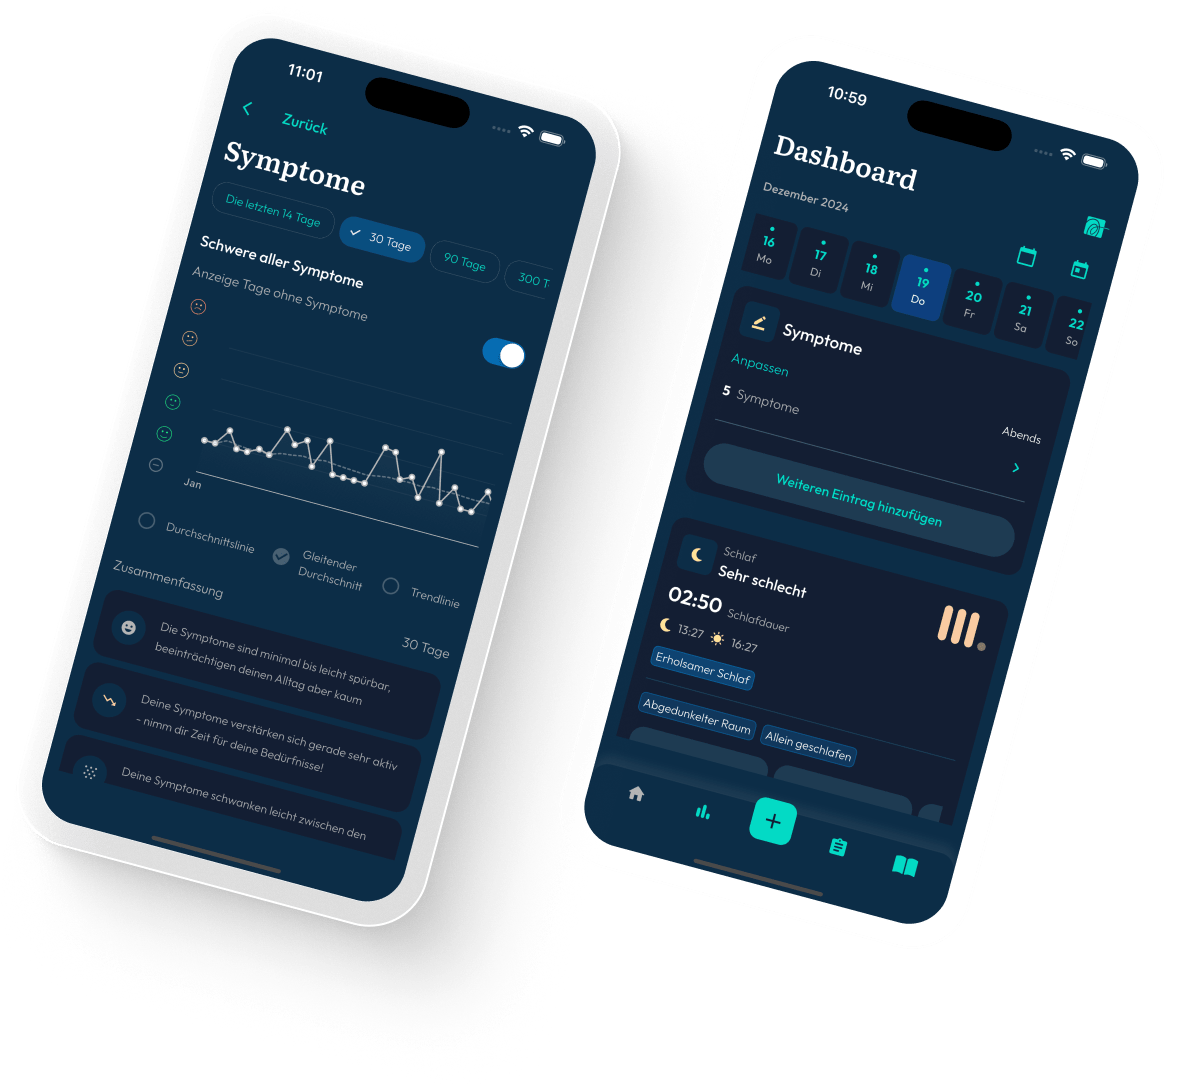
Record symptoms, exertion, and recovery to understand your trajectory – with the Elara app.
FAQ
Does every Long COVID case eventually become ME/CFS?
No. Long COVID remains a broad umbrella term. Only some courses develop a clearly ME/CFS-like pattern.
What is the strongest clue that the course is becoming more ME/CFS-like?
PEM is one of the strongest clues, especially when activity repeatedly leads to delayed and marked worsening.
Why does this matter so much in daily life?
Because load management, pacing, and cautious planning become much more important once activity itself is part of the problem.
Do you need a formal diagnosis before this pattern becomes relevant?
No. In daily life, the important issue often appears earlier: whether PEM, reduced capacity, and difficult recovery are shaping the course. That pattern can matter even before formal diagnostic clarification is complete.
Editorial standards
The linked guidelines and institutional resources explain the medical background. Editorial responsibility and any documented medical review are identified separately.
Medical background: 3 sources
Educational context – not a substitute for medical diagnosis
Links to related knowledge, questionnaires, and methodology